00 · START WITH THE NURSE'S COMPLAINT — THEN TEST IT
[Tier 2 / Allegation] THE COMPLAINT
A person identifying as a Sunrise nurse wrote that HCA was proposing 2.25% in year one and 2% in each of the next two years and asked for help exposing HCA.
[Boundary] The message is a lead. It is not proof of the employer's written offer, who is covered, total compensation, or what occurred at the bargaining table.
ONE-LINE SPEAKING SEQUENCE
1. Start with the nurse's claimed raise offer, then say the written proposal is still needed.
2. Establish that Sunrise is a for-profit HCA hospital, so the relevant public records are state filings, CMS data and HCA SEC filings — not Form 990.
3. Put Sunrise's local profit and HCA's shareholder returns beside the alleged wage proposal without pretending parent cash is facility cash.
4. Test whether the hospital expanded property and construction while frontline capacity tightened.
5. Explain the historical C safety grade accurately, including both bad and favorable component measures.
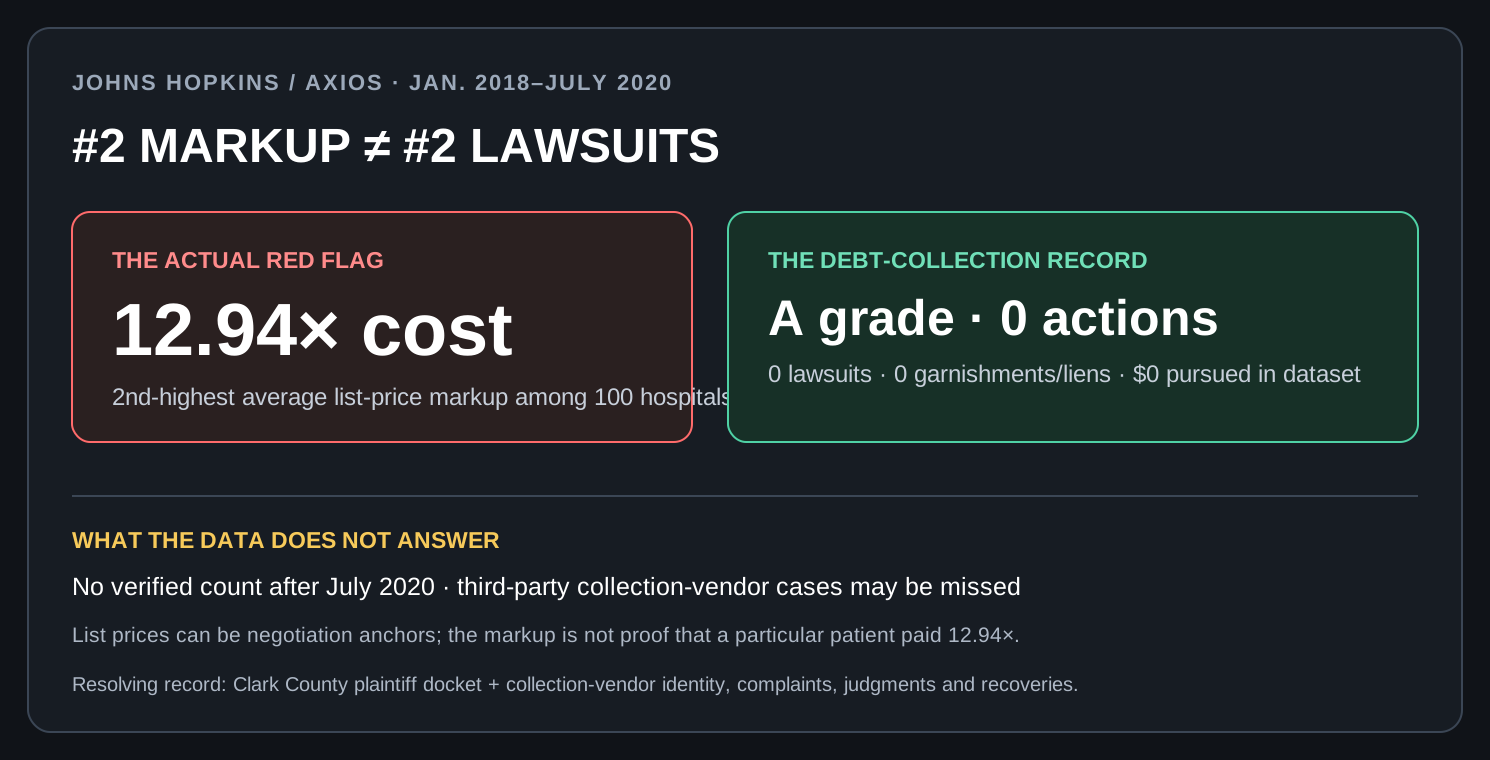
6. Correct the billing claim: Sunrise ranked second for markup, while the study found zero court actions.
7. Close with the documented audit, ADA settlement and open labor allegations, then demand the missing contracts and ledgers.
02
01 · START HERE — IDENTITY & SCOPE
SUNRISE HOSPITAL & MEDICAL CENTER
Las Vegas, Nevada · HCA Healthcare
Evidence map as of August 25, 2026
[Confirmed] This canvas concerns Sunrise Hospital and Medical Center, LLC at 3186 S. Maryland Parkway, Las Vegas — not a Los Angeles hospital.
[Scope] Sunrise facility money, HCA consolidated money, reimbursement, capital, investments and accounting balances stay in separate ledgers.
sunrise aerial official.png
[Confirmed] The legal hospital
Legal name: Sunrise Hospital and Medical Center, LLC
DBA: Sunrise Hospital & Medical Center
CCN: 290003
NPI: 1861439952
TIN/EIN: 62-1762537
Entity: Delaware LLC registered in Nevada on Jan. 12, 1999.
Tax status: proprietary / for-profit. It is not a 501(c)(3).
Connections:parent companyFY2025restricted vs affiliate holdings
04
03 · OWNERSHIP, CONTROL & PUBLIC FILINGS
[Confirmed] Full chain to the top
HCA Healthcare, Inc.
↓
HCA Inc.
↓
Healthtrust, Inc.–The Hospital Company
↓
AC Med, LLC
↓
Sunrise Hospital and Medical Center, LLC
[Analysis] HCA presents one operating brand, while legal filings preserve separate LLC layers. Entity shorthand is useful operationally but cannot prove which entity earned, paid or owed a dollar.
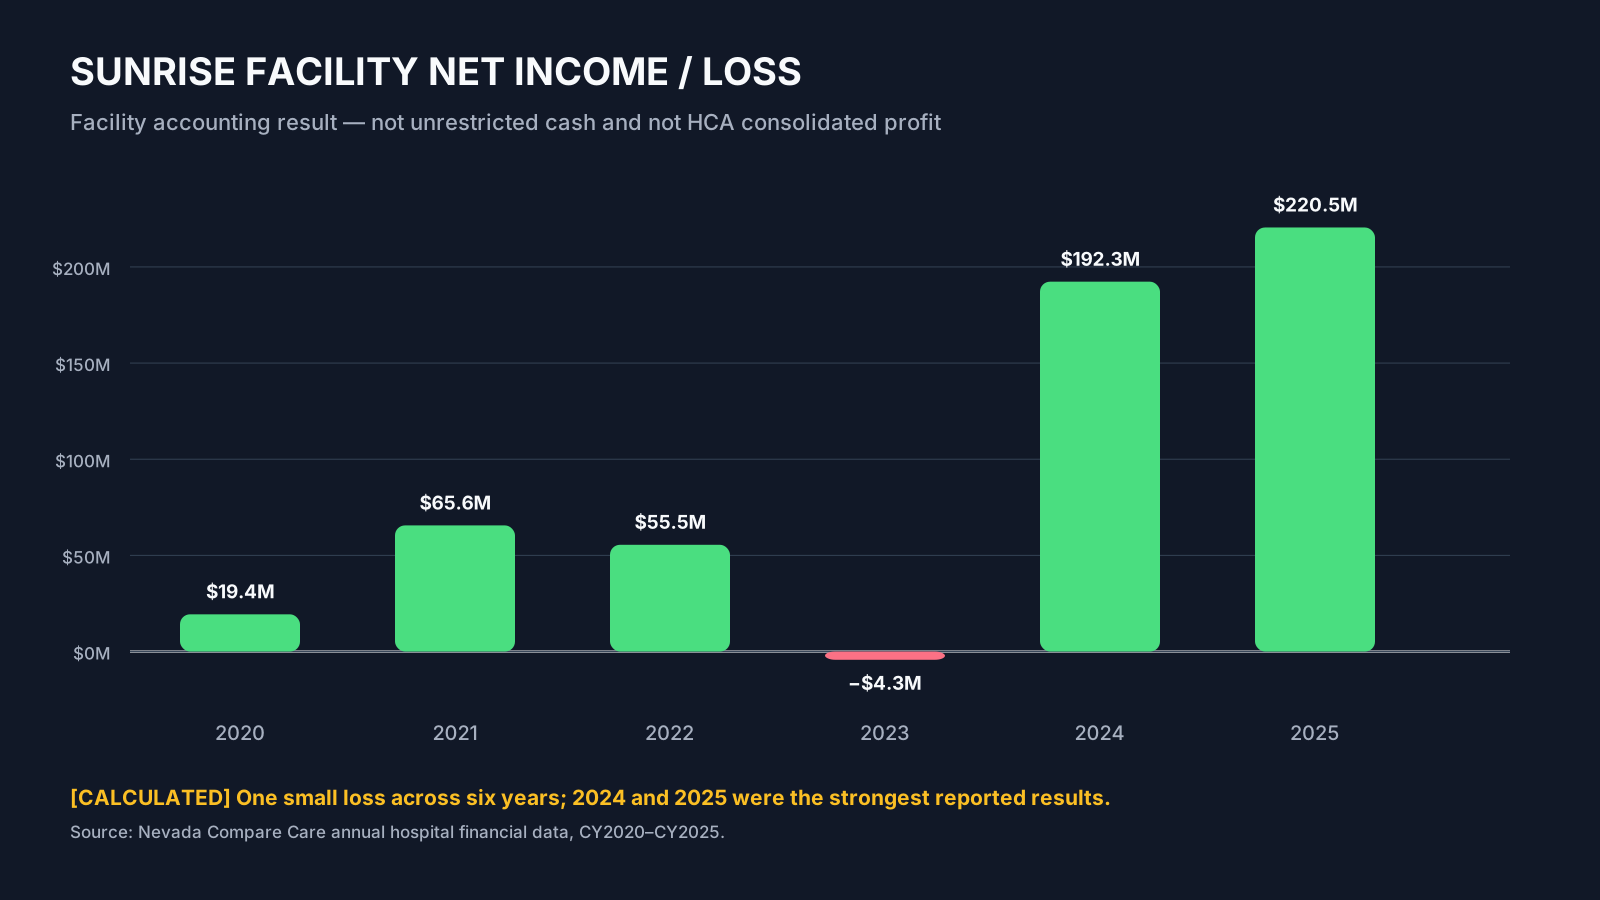
[Analysis] This is a Sunrise facility accounting result. It is not cash in a local bank account and not HCA’s consolidated profit.
[Confirmed with period caveat] Definitive Healthcare ranked Sunrise #8 among HCA hospitals using $799.754M of net patient revenue. It did not call the figure gross revenue, and the underlying service year is unclear.
[Discrepancy] Nevada reports $880.051M of CY2023 net patient revenue; period/method differences prevent direct comparison.
sunrise payer mix 2025.svg
[Analysis] Why the payer mix matters
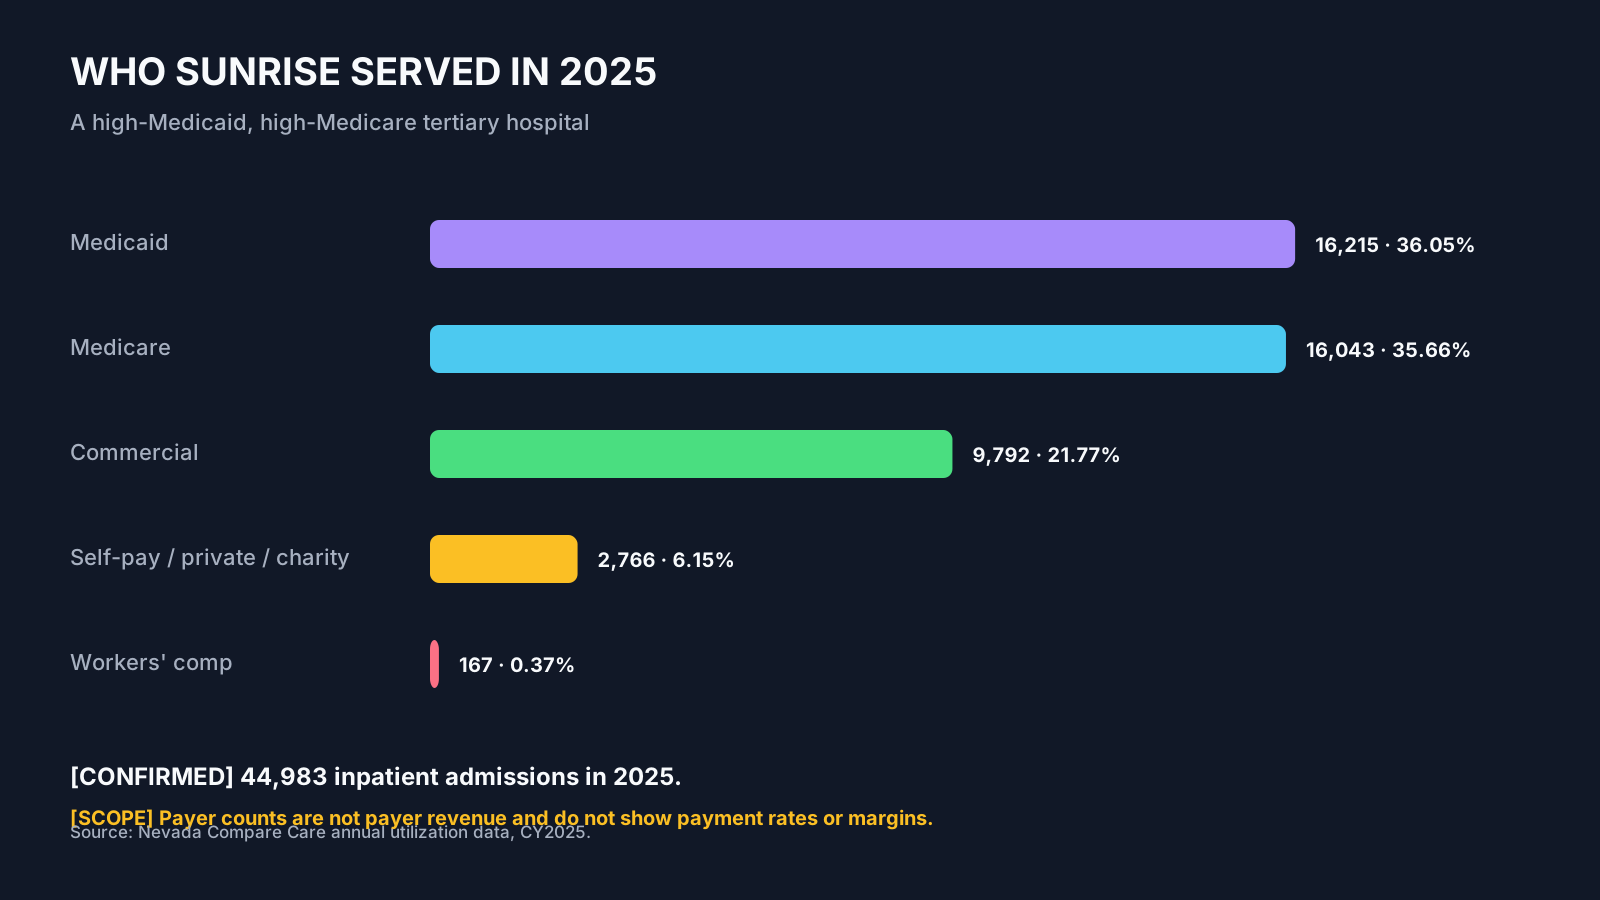
[Confirmed] Medicaid and Medicare together represented 71.71% of 2025 admissions.
[Analysis] Sunrise carries regional trauma and safety-net-like volume inside a for-profit chain. That can create legitimate rate and acuity pressure even when the facility and parent are profitable.
[Ethical mechanism] When staffed capacity falls behind demand, the cost is absorbed as waiting, boarding, floating and difficult assignments — not necessarily as measurable excess deaths.
Sunrise reported profits in 2020, 2021, 2022, 2024 and 2025, with a real but small $4.29M loss in 2023.
[Calculated] 2024→2025 revenue rose 5.40% and profit rose 14.66%.
[Innocent explanation tested] Rate changes, volume, acuity and Medicaid supplemental payments can move facility results sharply. The exact profit bridge is not public.
06 · WHERE THE MONEY WENT — AND WHAT IS NOT PUBLICLY DISCLOSED
[Confirmed] Parent-level beneficiaries
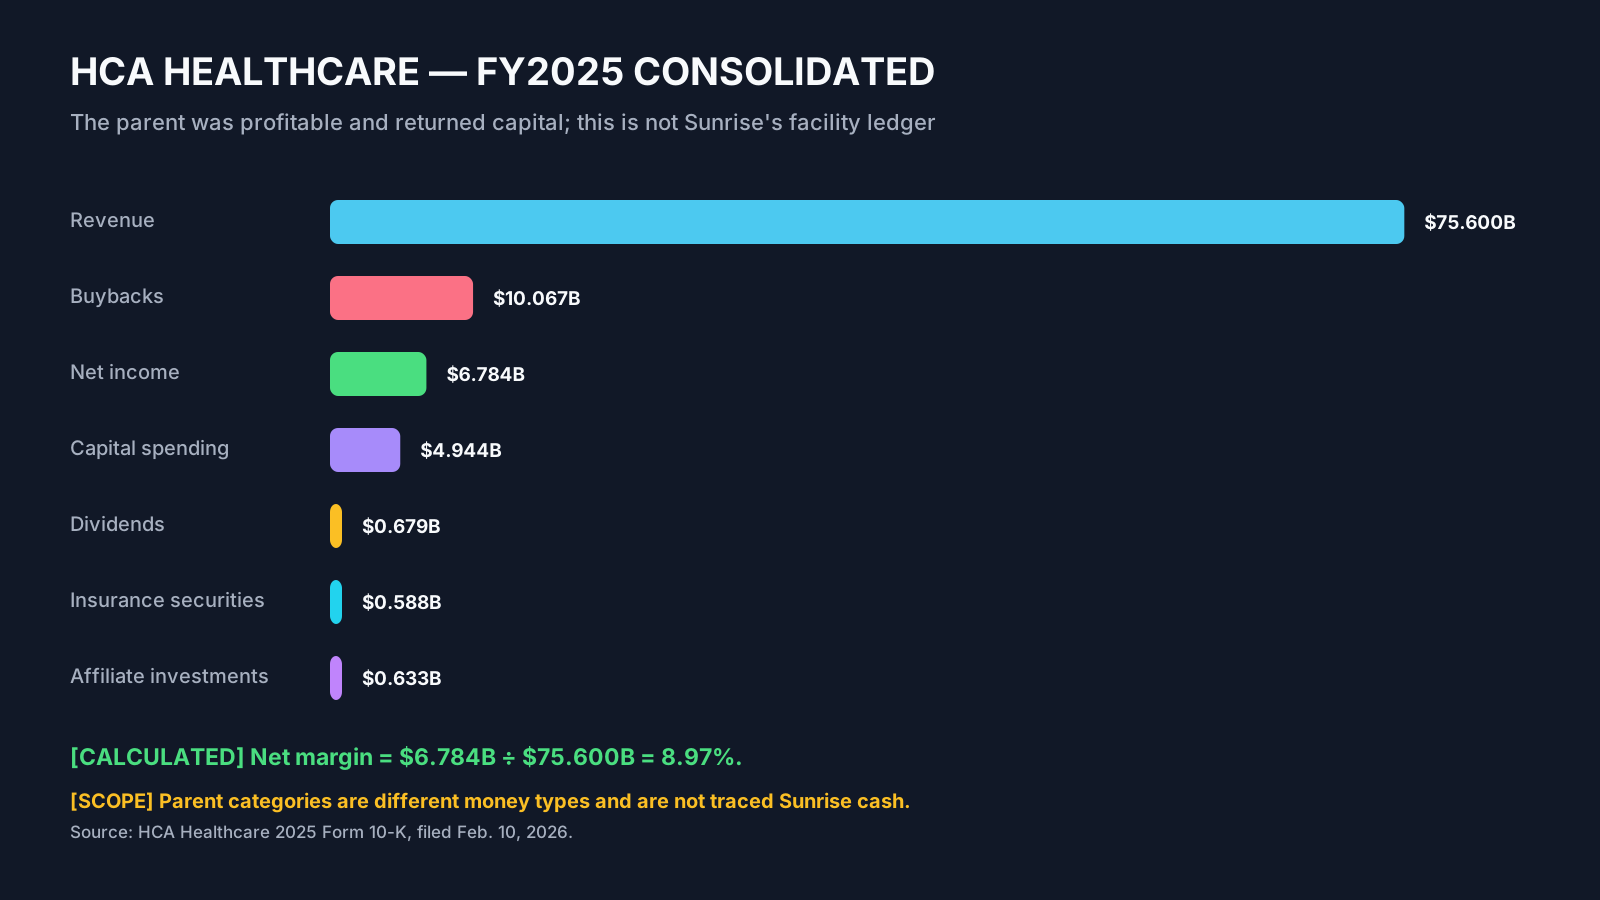
HCA shareholders: $10.067B buybacks + $679M dividends in 2025.
Sam Hazen: $26.457M total compensation in 2025.
Capital vendors systemwide: $4.944B HCA capital spending in 2025.
[Scope] These are consolidated HCA uses. No public journal traces Sunrise cash into them.
[Analysis] The tension is real — a profitable parent returned capital while local staffing pressure persisted — but the missing intercompany ledger prevents a diversion claim.
[Confirmed] Sunrise investment lines
For CY2023–CY2025, Sunrise’s state workbooks reported:
Marketable securities: $0
Interest/investment income: $0
JV/minority-interest income: $0
Gain on sale of assets: $0
Total non-operating revenue: $0
[Analysis] No Sunrise investment pool is visible in the facility return. This does not prove HCA lacks investments or that no affiliate holds Sunrise-related assets.
08
07 · REAL ESTATE, CAPITAL & EXPANSION
sunrise property book values 2023 2025.svg
[Confirmed] Visible capital deployment
Sunrise reported $47.304M of 2023 capital:
Expansions: $12.089M
Equipment: $3.825M
Other capital: $31.390M
[Calculated] $47.304M ÷ $39.728M depreciation = 119.07% for 2023.
[Scope] Capital money is not automatically available for wages; restrictions and financing sources were not disclosed.
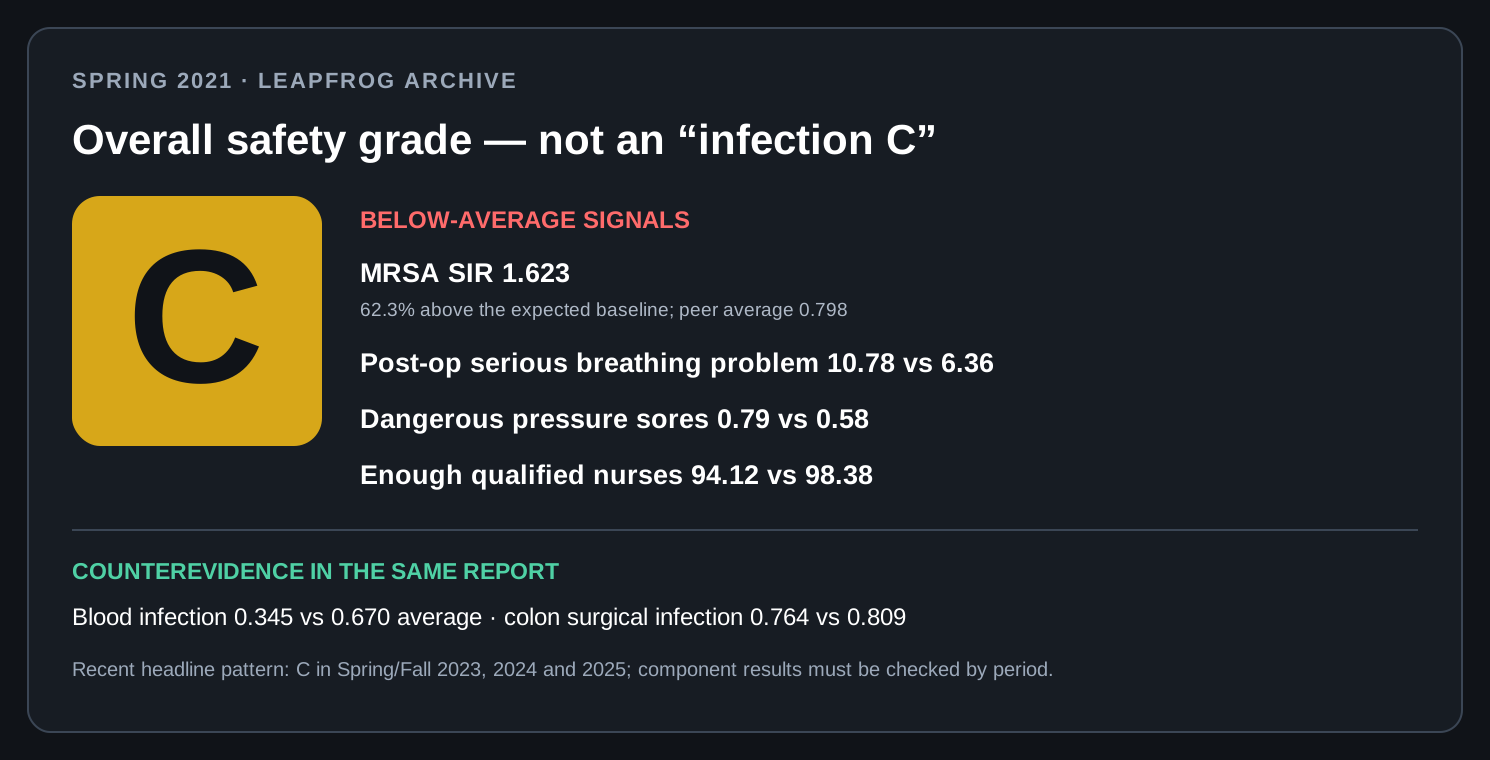
Sunrise received an overall Leapfrog Hospital Safety Grade of C in Spring 2021. The grade combined infections, surgery, safety practices, safety problems and doctors/nurses/staff; it was not a standalone infection grade.
[Confirmed] The same archive showed MRSA, serious post-operative breathing problems, pressure sores and qualified-nurse scoring below average, while blood infection and colon surgical-infection measures were favorable.
[Boundary] A C grade is a safety signal, not a death count or proof that staffing caused a specific injury.
[Confirmed] Pattern and time boundary
The official Leapfrog page shows C grades in both Spring and Fall of 2023, 2024 and 2025.
[Analysis] Repeated middling headline grades justify asking what stayed unresolved, but 2021 component scores cannot be presented as current.
[Innocent explanation tested] Component measures and methods change; recent infection measures are not uniformly poor.
OIG sampled 100 claims from a $41M high-risk universe and found 54 noncompliant before five reprocessings.
Refund recommendation: $23,606,895.
Sunrise disputed medical-necessity findings and extrapolation.
As of July 22, 2026, OIG’s tracker lists all three recommendations Closed Implemented.
[Verdict] A disputed audit and implemented refund recommendation — not a criminal fraud judgment.
2021
[Confirmed] Clark County imposed a $9,000 penalty for failure to perform required burner-efficiency tests.
[Innocent explanation] An isolated environmental testing lapse; no patient-harm intent shown.
2025
[Confirmed] DOJ ADA settlement: $30,000 damages + $5,000 civil penalty after denial of effective ASL communication to a deaf father during his daughter’s emergency visit.
[Allegation] NLRB case 28-CA-365427 remains open and alleges retaliation, discipline, unilateral changes, threats and surveillance. No merits finding.
[Confirmed] Historical HCA context — separate entity/time
DOJ described $1.7B in total government recoveries across HCA’s 2000–2003 criminal/civil resolutions; subsidiaries entered guilty pleas in 2000.
[Scope] This is relevant to parent compliance credibility. It does not prove Sunrise committed the same conduct, and HCA’s historical Corporate Integrity Agreement ended in 2009.
[Analysis] The pattern
The five-year record shows repeated contact with different oversight systems — billing, labor, disability access, environmental compliance and state reporting.
[Innocent explanation tested] These matters differ sharply in entity, legal posture and severity. The pattern supports scrutiny, not a single adjudicated corruption scheme.
11 · THE STORY, RED FLAGS & WHAT MUST BE DISCLOSED
THE ONE-PARAGRAPH STORY
[Confirmed] Sunrise is a large, high-Medicaid Level I trauma hospital inside HCA’s profitable public-company chain. It was profitable in five of the last six reported years and earned $220.5M in 2025, while HCA earned $6.784B and repurchased $10.067B of stock. The safety record shows a repeated C-grade headline pattern, but the billing study contradicts the claim that Sunrise was a leading patient-lawsuit filer: it was second for list-price markup and recorded zero court actions in the study period. Current mortality data reject a sensational death narrative. The decisive missing mechanisms are the written wage proposal, post-July-2020 collection docket and intercompany ledger.
[Confirmed] RED FLAGS FOUND
Layered parent/facility entity scope
$151.58M home-office allocations, 2022–2025
Near-zero facility cash with no cash-pool bridge
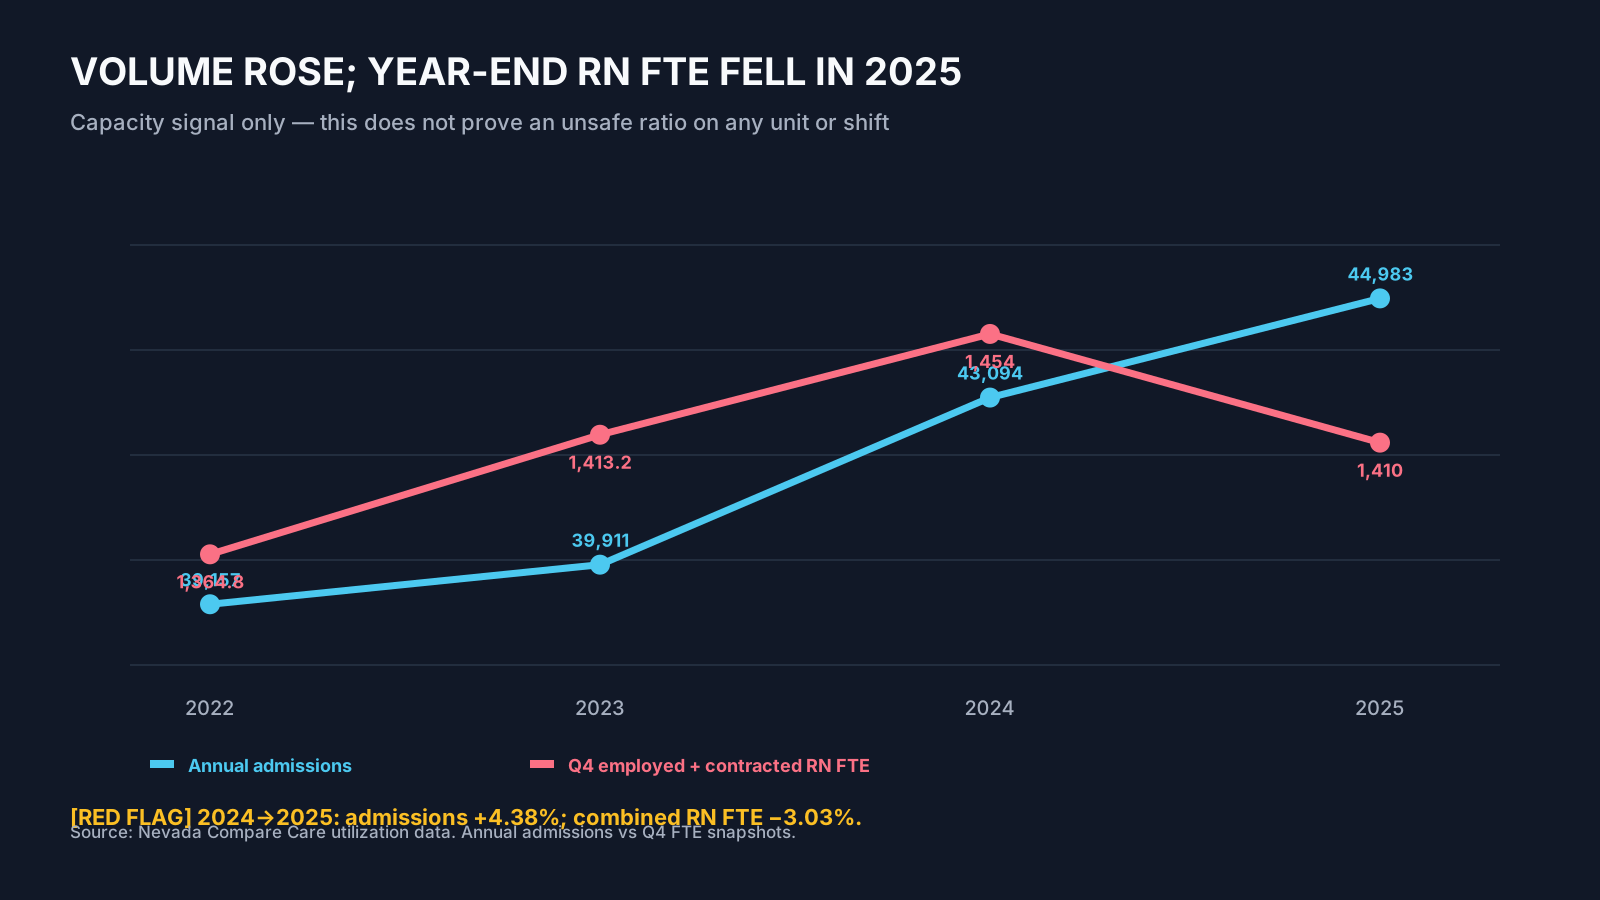
2025 admissions up while Q4 RN FTE fell
Unit-level overflow/out-of-ratio events
Overall Leapfrog C in 2021 and each Spring/Fall 2023–2025
12.94× list-price markup, second among 100 in the study
OIG refund recommendation, disputed then implemented/closed
Settled ADA communication failure
Open labor allegations
State report narrative-year contradiction
Parent buybacks/dividends during local access pressure
[Confirmed] NOT FOUND
Current PE ownership
Nonprofit / IRS Form 990 status
Verified sale-leaseback or PropCo
Current service closure
Going-concern warning
Excess-mortality finding
Verified immediate-jeopardy cluster
Second-highest patient-lawsuit rank in the 100-hospital study
Any Sunrise court action in the Jan. 2018–July 2020 study period
Active Corporate Integrity Agreement
Adjudicated labor-retaliation finding
Proof Sunrise cash funded HCA buybacks
Connections:resolving documents
Canvas 2
Sunrise Hospital comprehensive research canvas
The deeper Las Vegas research canvas with wage, contractor, benefit, financial-turnaround, and accountability materials.
01 · START HERE — SUNRISE 2023 LOSS → 2025 PROFIT-SOURCE AUDIT
PRIORITY 1 · SUNRISE-ONLY FINANCIAL AUDIT
What caused the 2023 loss—and where did the 2025 profit come from?
Plain answer: 2023 was primarily a cost/revenue squeeze, the 2024 rebound aligns strongly with a major increase in Nevada Medicaid supplemental reimbursement, and the 2025 $220.5M result came from operating patient-care revenue—not investment income. High list prices remain a serious audit question, but public summary data do not prove illegal patient overcharging.
Scope lock: every number in this section is Sunrise Hospital Las Vegas or HCA parent context. No benefit or parking percentage from another institution is included.
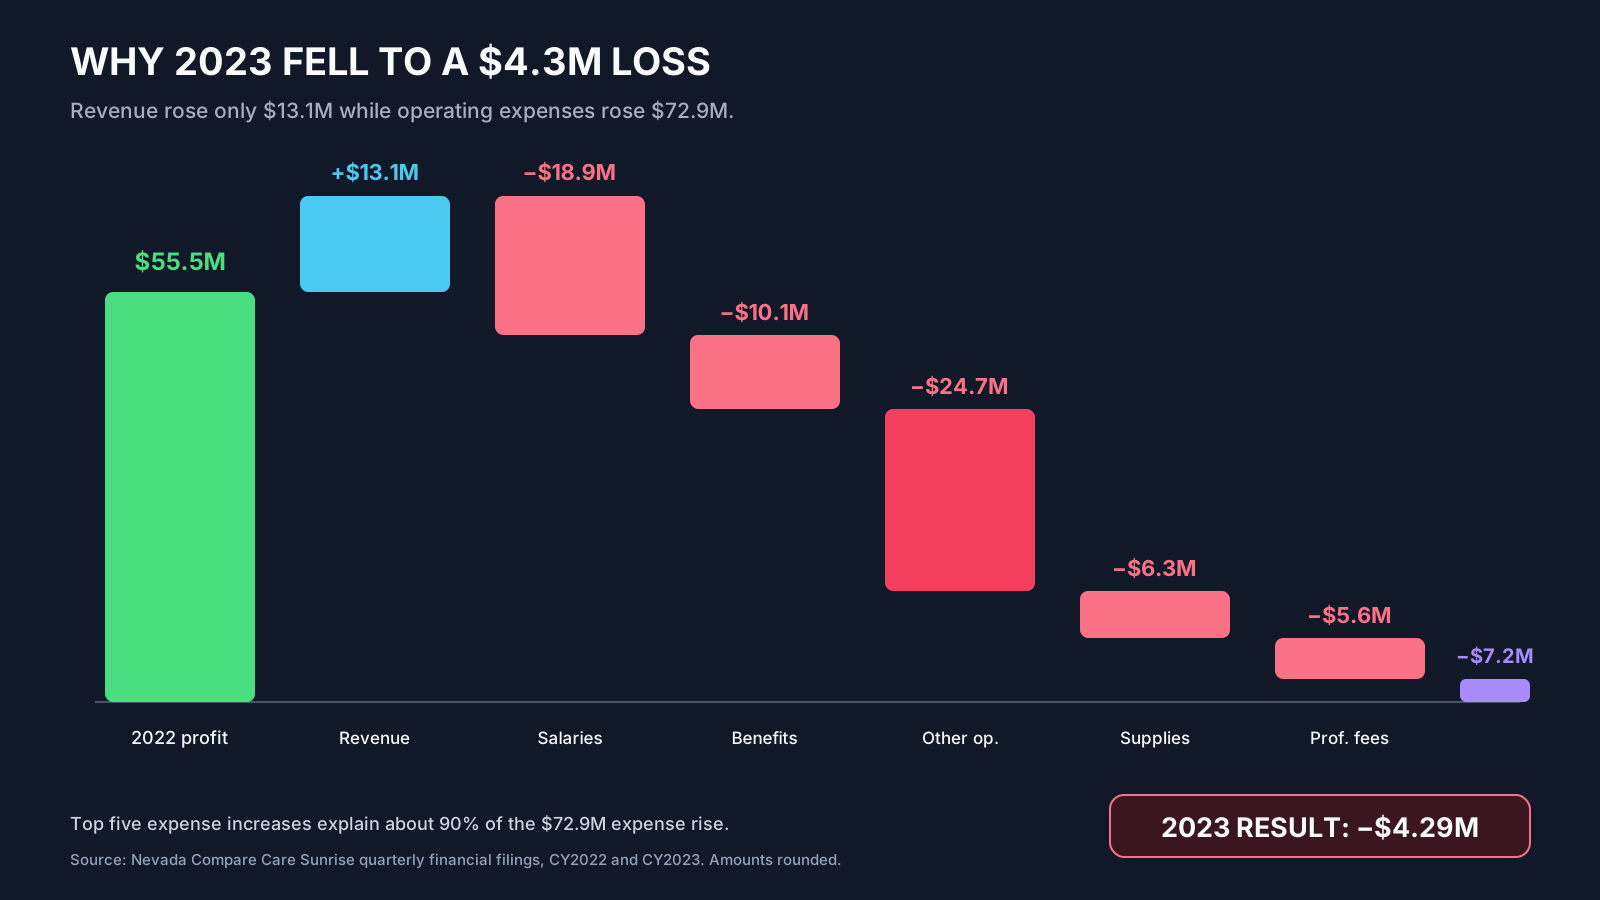
1A · Why did +$55.5M become −$4.3M in 2023?
Revenue: +$13.075M (+1.50%)
Expenses: +$72.869M (+8.92%)
Profit change: −$59.794M
Largest expense increases: other operating +$24.739M; salaries +$18.893M; benefits +$10.118M; supplies +$6.333M; professional fees +$5.552M. Together: $65.635M, or 90.1% of the expense increase.
Verdict: the −$4.288M was the residual after expenses outran revenue—not a separate hidden $4.3M transaction.
1B · What most likely drove the 2024 rebound?
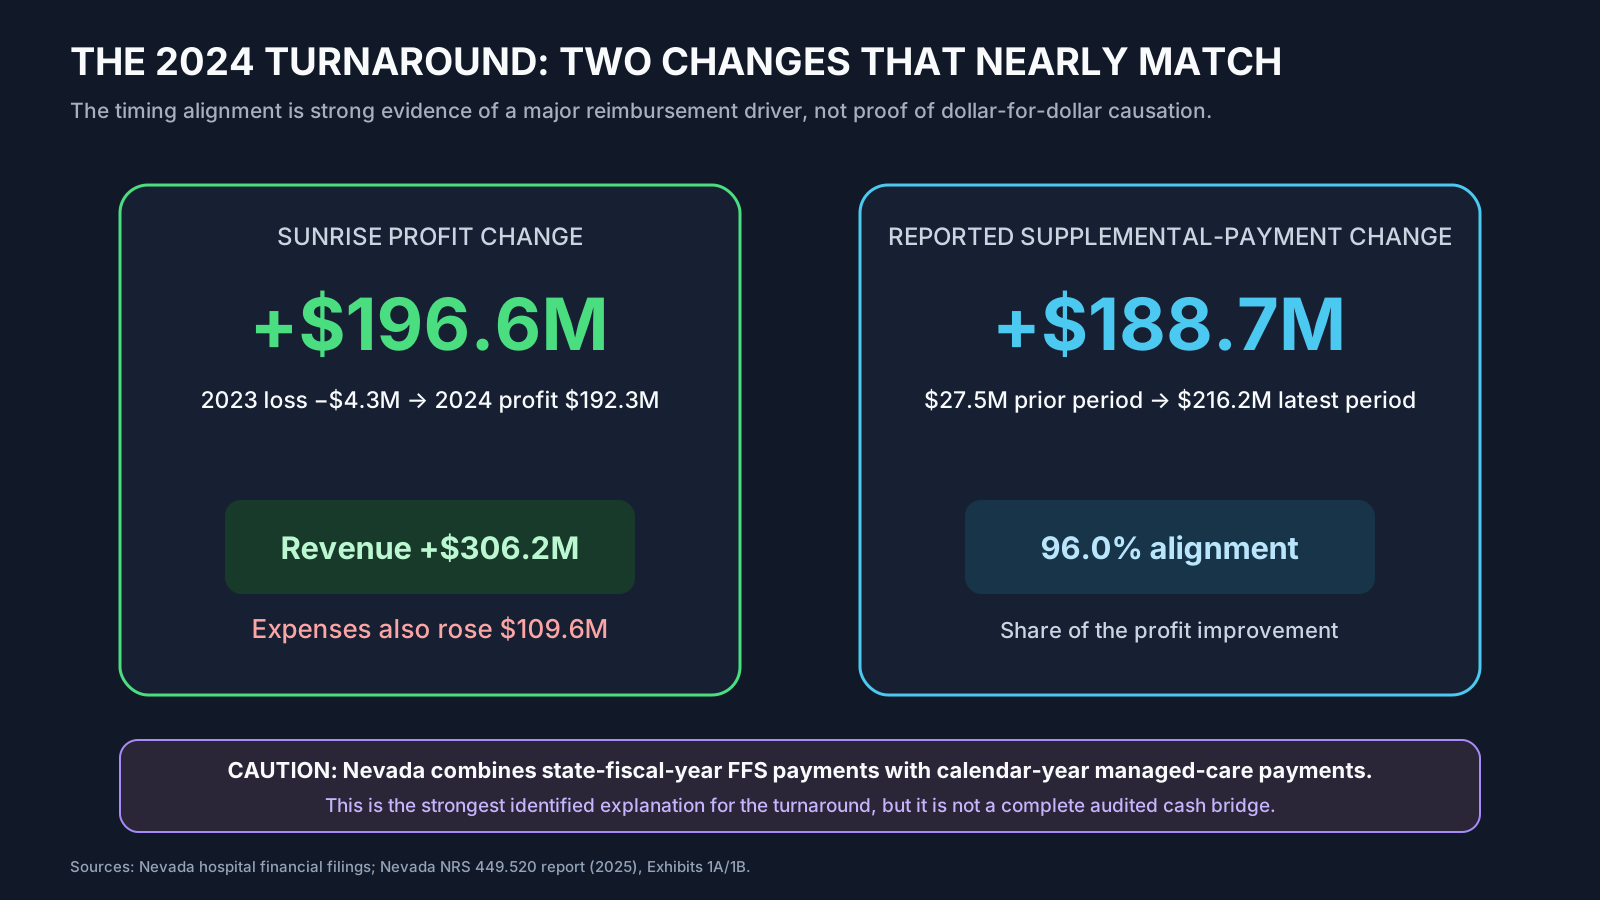
2023→2024 operating revenue increased $306.246M, expense increased $109.640M, and profit improved $196.606M to +$192.318M.
Nevada’s combined-period supplemental-payment report shows Sunrise rising from $27.511M to $216.202M: +$188.692M, equal to 96.0% of the profit improvement.
Boundary: this is compelling alignment, not audited causation. The state report mixes SFY fee-for-service and CY managed-care periods; assessments/provider taxes, patient volume, rates and acuity also matter.
1C · Where did the 2025 $220.5M profit come from?
Net patient revenue: $1.250603B
Other operating revenue: $5.713M
Operating revenue: $1.256316B
Operating expenses: $1.035812B
Net income:$220.504M (17.55%)
Inpatient net revenue was $953.516M (76.24%); outpatient was $297.087M (23.76%). Reported non-operating revenue was $0.
Conclusion: the profit is an operating patient-care margin. The public workbook does not disclose payer-level margins, cash collections, or service-line profitability.
1D · Overcharging test + what would 5% or 6% cost?
2025 list charges $15.709B minus deductions $14.459B (92.04%) left $1.251B net patient revenue (7.96% of list). This confirms extreme gross-to-net compression; it does not establish what individual patients paid or prove illegality.
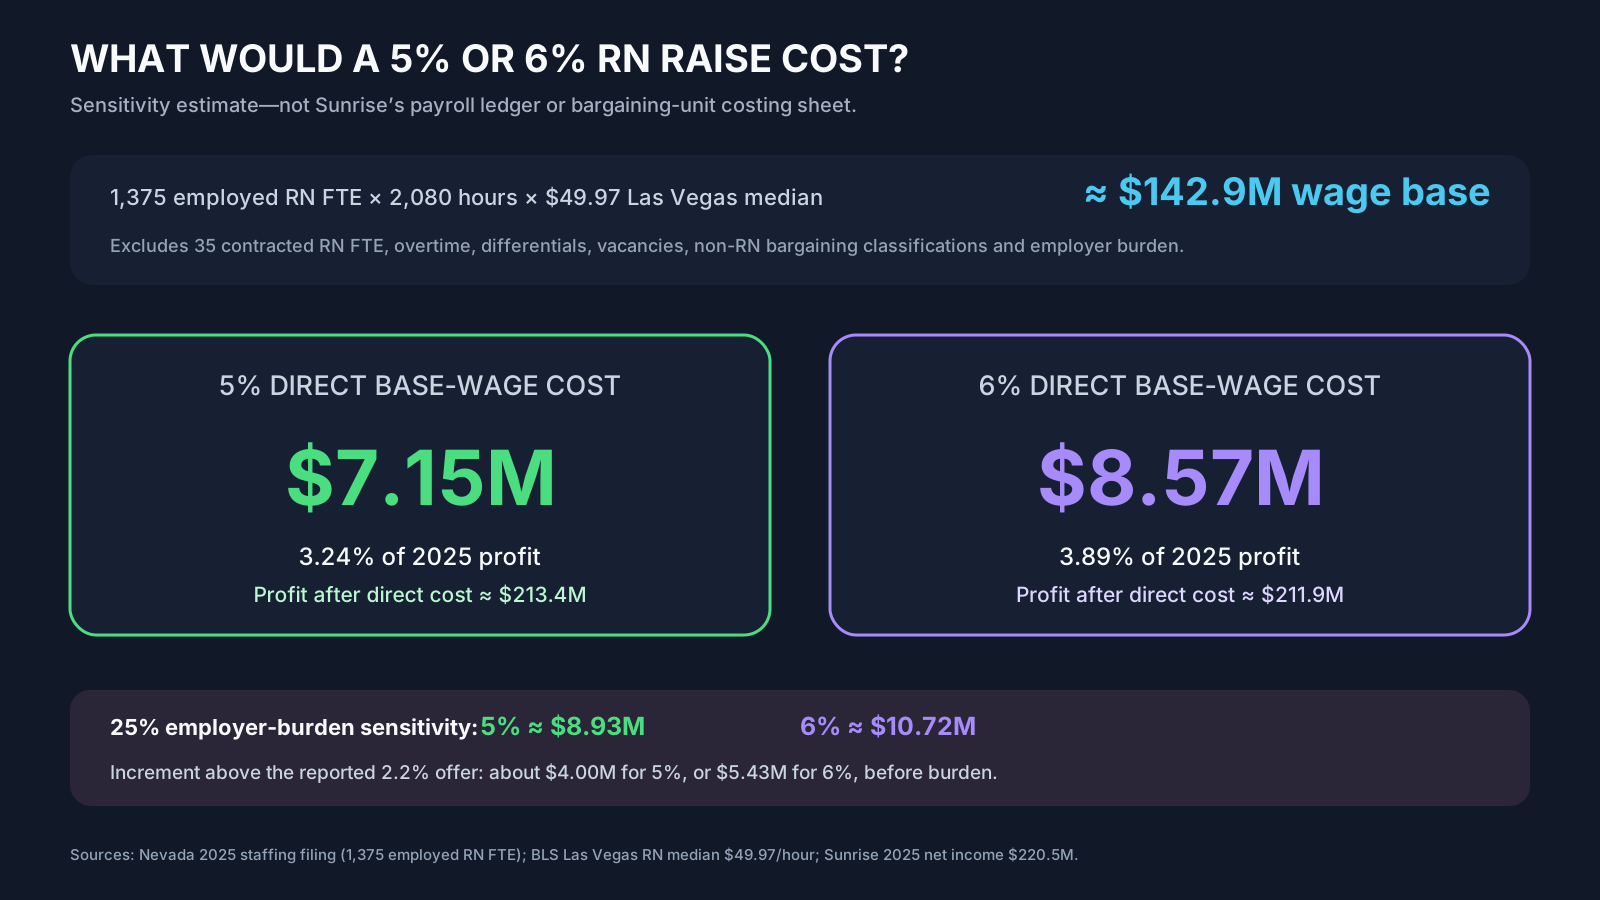
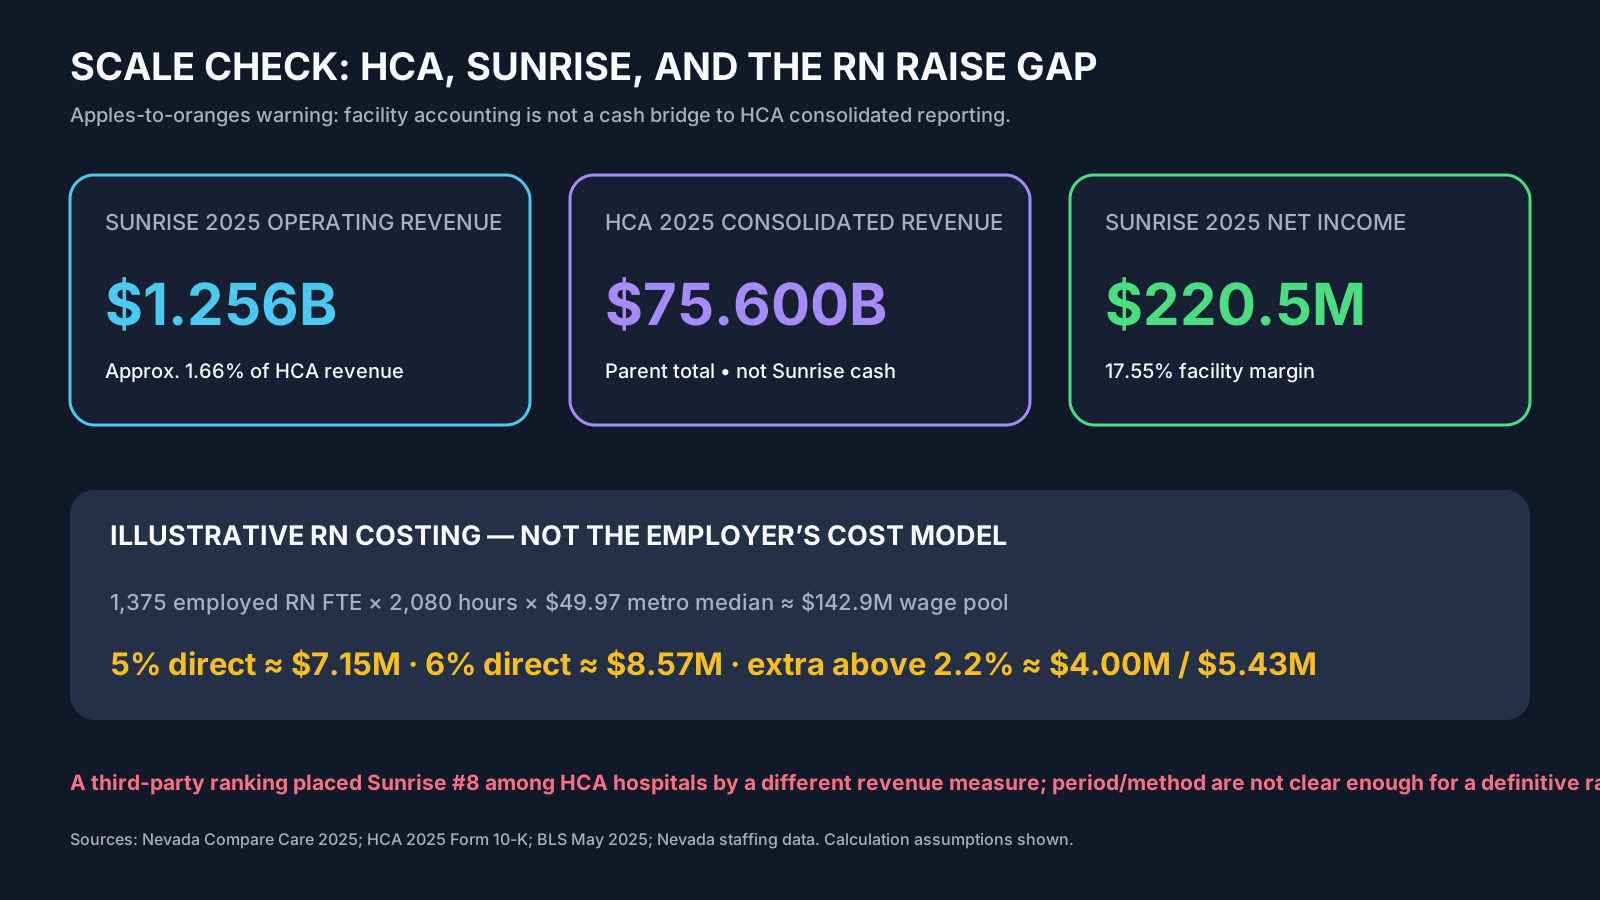
Using 1,375 employed RN FTE, BLS median $49.97/hr, and 2,080 hours: estimated RN base-pay pool $142.9M.
5%: $7.15M direct; $8.93M with 25% burden.
6%: $8.57M direct; $10.72M with burden.
Direct cost equals 3.24% / 3.89% of 2025 profit. Extra above 2.2%: $4.00M / $5.43M. Agency RNs and non-RN classifications excluded.
Connections:FY2025restricted vs affiliate holdings
04
04 · OWNERSHIP, CONTROL & PUBLIC FILINGS
[Confirmed] Full chain to the top
HCA Healthcare, Inc.
↓
HCA Inc.
↓
Healthtrust, Inc.–The Hospital Company
↓
AC Med, LLC
↓
Sunrise Hospital and Medical Center, LLC
[Analysis] HCA presents one operating brand, while legal filings preserve separate LLC layers. Entity shorthand is useful operationally but cannot prove which entity earned, paid or owed a dollar.
[Analysis] This is a Sunrise facility accounting result. It is not cash in a local bank account and not HCA’s consolidated profit.
[Confirmed with period caveat] Definitive Healthcare ranked Sunrise #8 among HCA hospitals using $799.754M of net patient revenue. It did not call the figure gross revenue, and the underlying service year is unclear.
[Discrepancy] Nevada reports $880.051M of CY2023 net patient revenue; period/method differences prevent direct comparison.
sunrise payer mix 2025.svg
[Analysis] Why the payer mix matters
[Confirmed] Medicaid and Medicare together represented 71.71% of 2025 admissions.
[Analysis] Sunrise carries regional trauma and safety-net-like volume inside a for-profit chain. That can create legitimate rate and acuity pressure even when the facility and parent are profitable.
[Ethical mechanism] When staffed capacity falls behind demand, the cost is absorbed as waiting, boarding, floating and difficult assignments — not necessarily as measurable excess deaths.
[Confirmed] Medicaid reimbursement explains much of the rebound
Nevada’s combined-period report shows Sunrise supplemental payments rising from $27.511M to $216.202M — an increase of $188.692M.
[Calculated] That equals 96.0% of the $196.606M improvement from the 2023 loss to the 2024 profit.
[Scope] This is a strong accounting alignment, not dollar-for-dollar proof: the report combines state-fiscal-year FFS and calendar-year MCO periods. Assessments/provider taxes and other operating changes still require reconciliation.
07 · WHERE THE MONEY WENT — AND WHAT IS NOT PUBLICLY DISCLOSED
[Confirmed] Parent-level beneficiaries
HCA shareholders: $10.067B buybacks + $679M dividends in 2025.
Sam Hazen: $26.457M total compensation in 2025.
Capital vendors systemwide: $4.944B HCA capital spending in 2025.
[Scope] These are consolidated HCA uses. No public journal traces Sunrise cash into them.
[Analysis] The tension is real — a profitable parent returned capital while local staffing pressure persisted — but the missing intercompany ledger prevents a diversion claim.
[Confirmed] Sunrise investment lines
For CY2023–CY2025, Sunrise’s state workbooks reported:
Marketable securities: $0
Interest/investment income: $0
JV/minority-interest income: $0
Gain on sale of assets: $0
Total non-operating revenue: $0
[Analysis] No Sunrise investment pool is visible in the facility return. This does not prove HCA lacks investments or that no affiliate holds Sunrise-related assets.
08
08 · REAL ESTATE, CAPITAL & EXPANSION
sunrise property book values 2023 2025.svg
[Confirmed] Visible capital deployment
Sunrise reported $47.304M of 2023 capital:
Expansions: $12.089M
Equipment: $3.825M
Other capital: $31.390M
[Calculated] $47.304M ÷ $39.728M depreciation = 119.07% for 2023.
[Scope] Capital money is not automatically available for wages; restrictions and financing sources were not disclosed.
OIG sampled 100 claims from a $41M high-risk universe and found 54 noncompliant before five reprocessings.
Refund recommendation: $23,606,895.
Sunrise disputed medical-necessity findings and extrapolation.
As of July 22, 2026, OIG’s tracker lists all three recommendations Closed Implemented.
[Verdict] A disputed audit and implemented refund recommendation — not a criminal fraud judgment.
2021
[Confirmed] Clark County imposed a $9,000 penalty for failure to perform required burner-efficiency tests.
[Innocent explanation] An isolated environmental testing lapse; no patient-harm intent shown.
2025
[Confirmed] DOJ ADA settlement: $30,000 damages + $5,000 civil penalty after denial of effective ASL communication to a deaf father during his daughter’s emergency visit.
[Allegation] NLRB case 28-CA-365427 remains open and alleges retaliation, discipline, unilateral changes, threats and surveillance. No merits finding.
[Confirmed] Historical HCA context — separate entity/time
DOJ described $1.7B in total government recoveries across HCA’s 2000–2003 criminal/civil resolutions; subsidiaries entered guilty pleas in 2000.
[Scope] This is relevant to parent compliance credibility. It does not prove Sunrise committed the same conduct, and HCA’s historical Corporate Integrity Agreement ended in 2009.
[Analysis] The pattern
The five-year record shows repeated contact with different oversight systems — billing, labor, disability access, environmental compliance and state reporting.
[Innocent explanation tested] These matters differ sharply in entity, legal posture and severity. The pattern supports scrutiny, not a single adjudicated corruption scheme.
Connections:entity/time boundary
11
11 · THE STORY, RED FLAGS & WHAT MUST BE DISCLOSED
THE ONE-PARAGRAPH STORY
[Confirmed] Sunrise is a large, high-Medicaid Level I trauma hospital inside HCA’s profitable public-company chain. It was profitable in five of the last six reported years and earned $220.5M in 2025, while HCA earned $6.784B and repurchased $10.067B of stock. Sunrise’s own record also shows a 2025 staffing-volume divergence, earlier unit-level overflow, weaker readmission/satisfaction signals, an ADA access failure and recurring oversight. Current mortality data reject a sensational death narrative. The decisive missing mechanism is the intercompany ledger: who controlled Sunrise cash, how home-office costs were allocated, and whether local staffing and capital decisions competed with parent priorities.
[Confirmed] RED FLAGS FOUND
Layered parent/facility entity scope
$151.58M home-office allocations, 2022–2025
Near-zero facility cash with no cash-pool bridge
2025 admissions up while Q4 RN FTE fell
Unit-level overflow/out-of-ratio events
OIG refund recommendation, disputed then implemented/closed
Settled ADA communication failure
Open labor allegations
State report narrative-year contradiction
Parent buybacks/dividends during local access pressure
[Confirmed] NOT FOUND
Current PE ownership
Nonprofit / IRS Form 990 status
Verified sale-leaseback or PropCo
Current service closure
Going-concern warning
Excess-mortality finding
Verified immediate-jeopardy cluster
Active Corporate Integrity Agreement
Adjudicated labor-retaliation finding
Proof Sunrise cash funded HCA buybacks
Connections:resolving documents
12
12 · NURSE PAY, COST OF LIVING & CONTRACT ACCOUNTABILITY — AUG. 2026
fox5 sunrise contract rally 2026.png
Q1 · What is the normal RN wage at Sunrise?
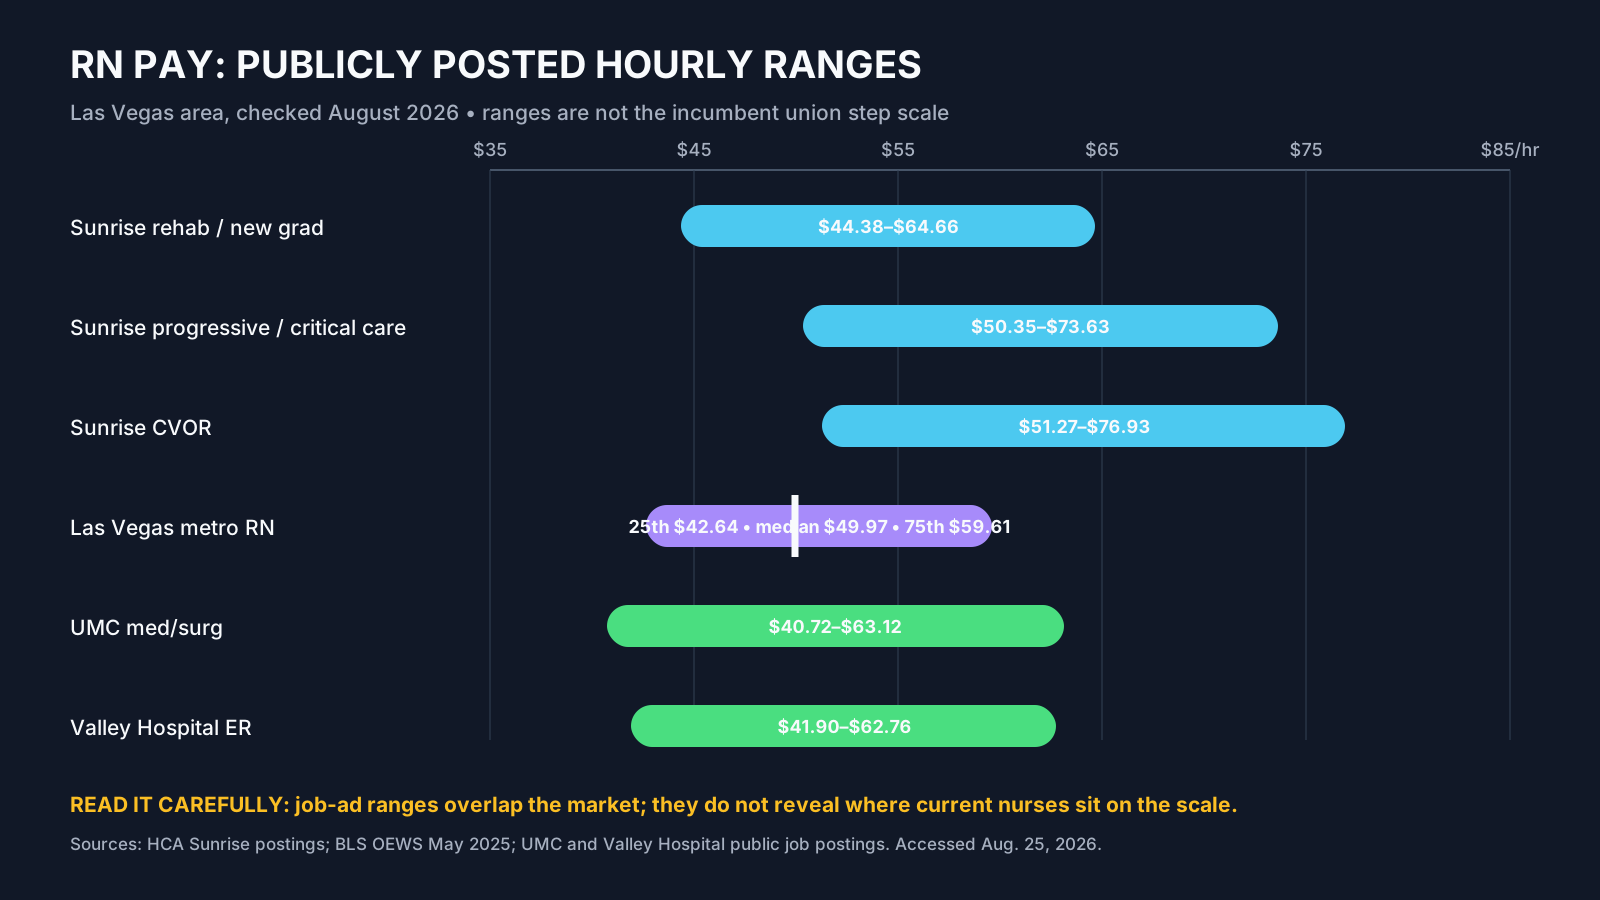
[Verified public job ranges]
Rehab / new graduate: $44.38–$64.66/hr
Progressive / critical care: $50.35–$73.63/hr
CVOR: $51.27–$76.93/hr
Answer: These postings show hiring ranges, not the actual pay of incumbent union nurses or the contract step scale. The ranges overlap the Las Vegas market, but cannot prove that current nurses are paid at market.
Source: HCA Sunrise job postings, checked Aug. 2026. Missing: current CBA wage grid and employee pay-step distribution.
Q2 · What do Las Vegas nurses make, and what is inflation?
BLS Las Vegas RN pay (May 2025): 25th $42.64, median $49.97, 75th $59.61, 90th $64.07/hr. Peer postings: UMC med/surg $40.72–$63.12; Valley ER $41.90–$62.76.
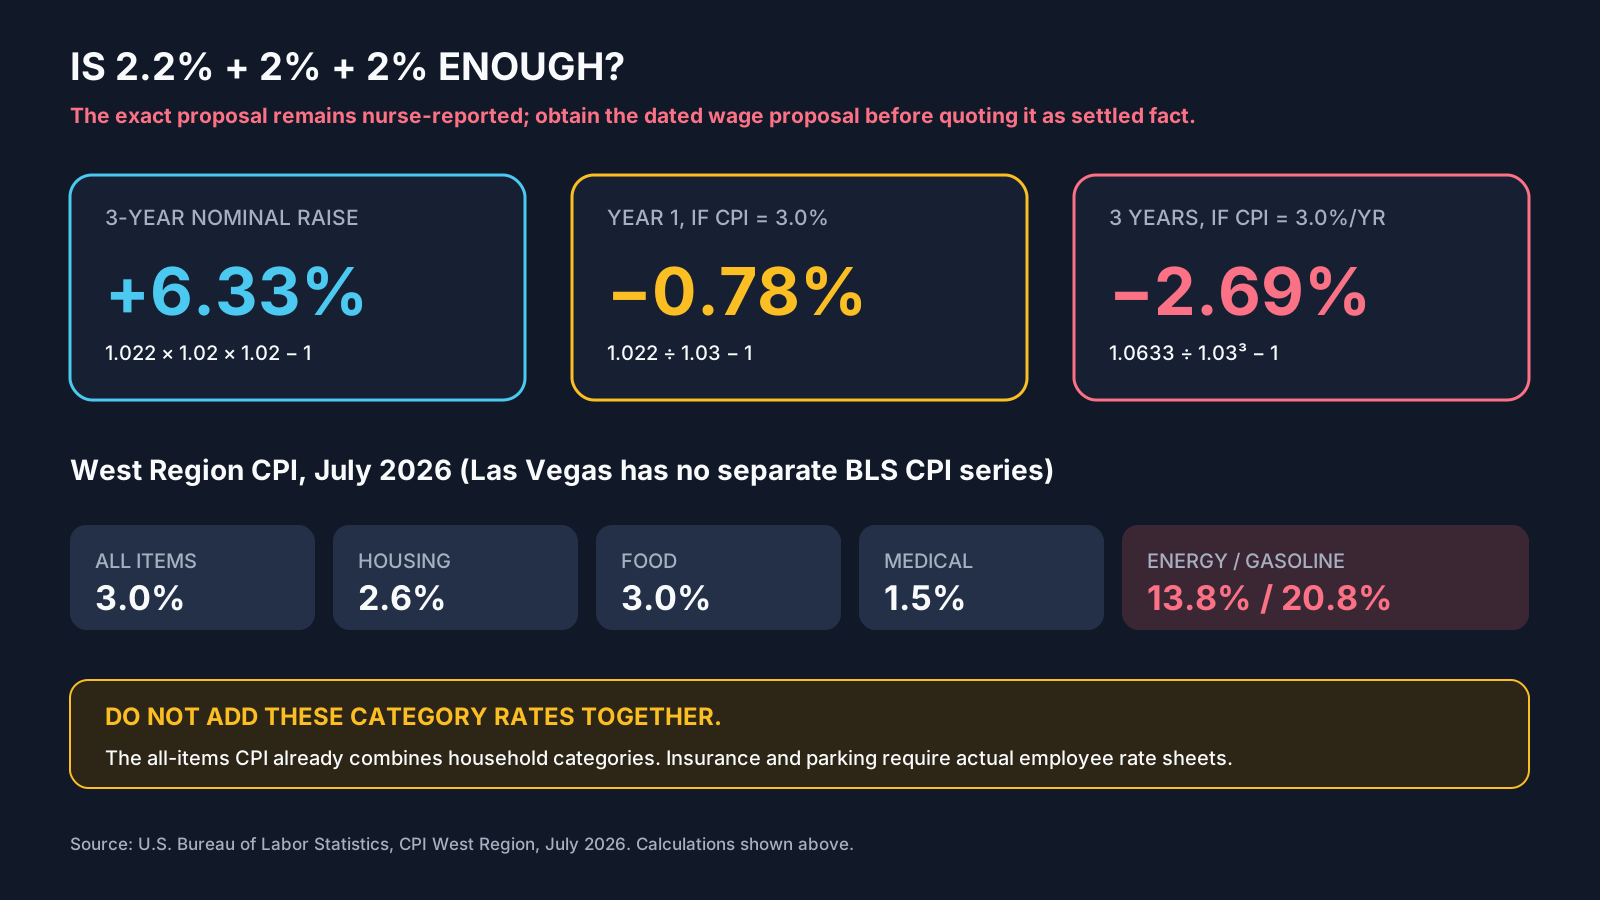
BLS does not publish a Las Vegas CPI. The best official proxy, West Region CPI (July 2026), was 3.0% overall; housing 2.6%, food 3.0%, medical care 1.5%, energy 13.8%, gasoline 20.8%.
Do not add category inflation rates together: the 3.0% index already combines them.
nurse pay market comparison 2026.svgraise vs inflation 2026.svg
Q4 · Is 2.2% / 2% / 2% enough?
[Calculated from the Sunrise nurse-reported proposal] Compounded nominal growth over three years is 6.33%.
If inflation is 3.0%:
Year 1 purchasing power: −0.78%
Three-year purchasing power, if CPI stays 3% each year: −2.69%
Answer: On that scenario, the offer does not preserve purchasing power. Any Sunrise-specific insurance or parking change must be added only after the actual rate sheets are obtained.
Important: obtain the dated proposal; do not publish the percentages as a verified employer offer without it.
Q5 · Is Sunrise financially hanging by a thread?
[Verified facility accounting] 2025: revenue $1.256B; expenses $1.036B; net income $220.5M; margin 17.55%.
Net income: 2020 $19.4M; 2021 $65.6M; 2022 $55.5M; 2023 −$4.3M; 2024 $192.3M; 2025 $220.5M. Sunrise was profitable in 5 of 6 years.
2023 was a squeeze, not a hidden $4.3M: revenue rose 1.50%, expenses rose 8.92%. The biggest increases were other operating expense, salaries, benefits, supplies and professional fees.
Answer: The public figures show a strong rebound, not an institution on the edge of collapse. Net income is not unrestricted cash, but management should explain any contrary claim.
Q6 · Was there a $223M Medicare-fraud prosecution?
No public record located supports that wording. HHS OIG audit A-04-19-08075 reviewed selected high-risk claims from 2017–2018. In a 100-claim sample, OIG found 54 noncompliant claims and recommended a $23,606,895 extrapolated net refund. The sampled overpayment was $999,950.
Sunrise disputed the findings. This was an audit and refund recommendation, not a $223M criminal fraud conviction or prosecution.
Source image below: first page of the official HHS OIG audit brief.
Rule: describe audit findings, management response and adjudicative status separately.
Q7 · What is Sunrise investing in? Is it extravagant?
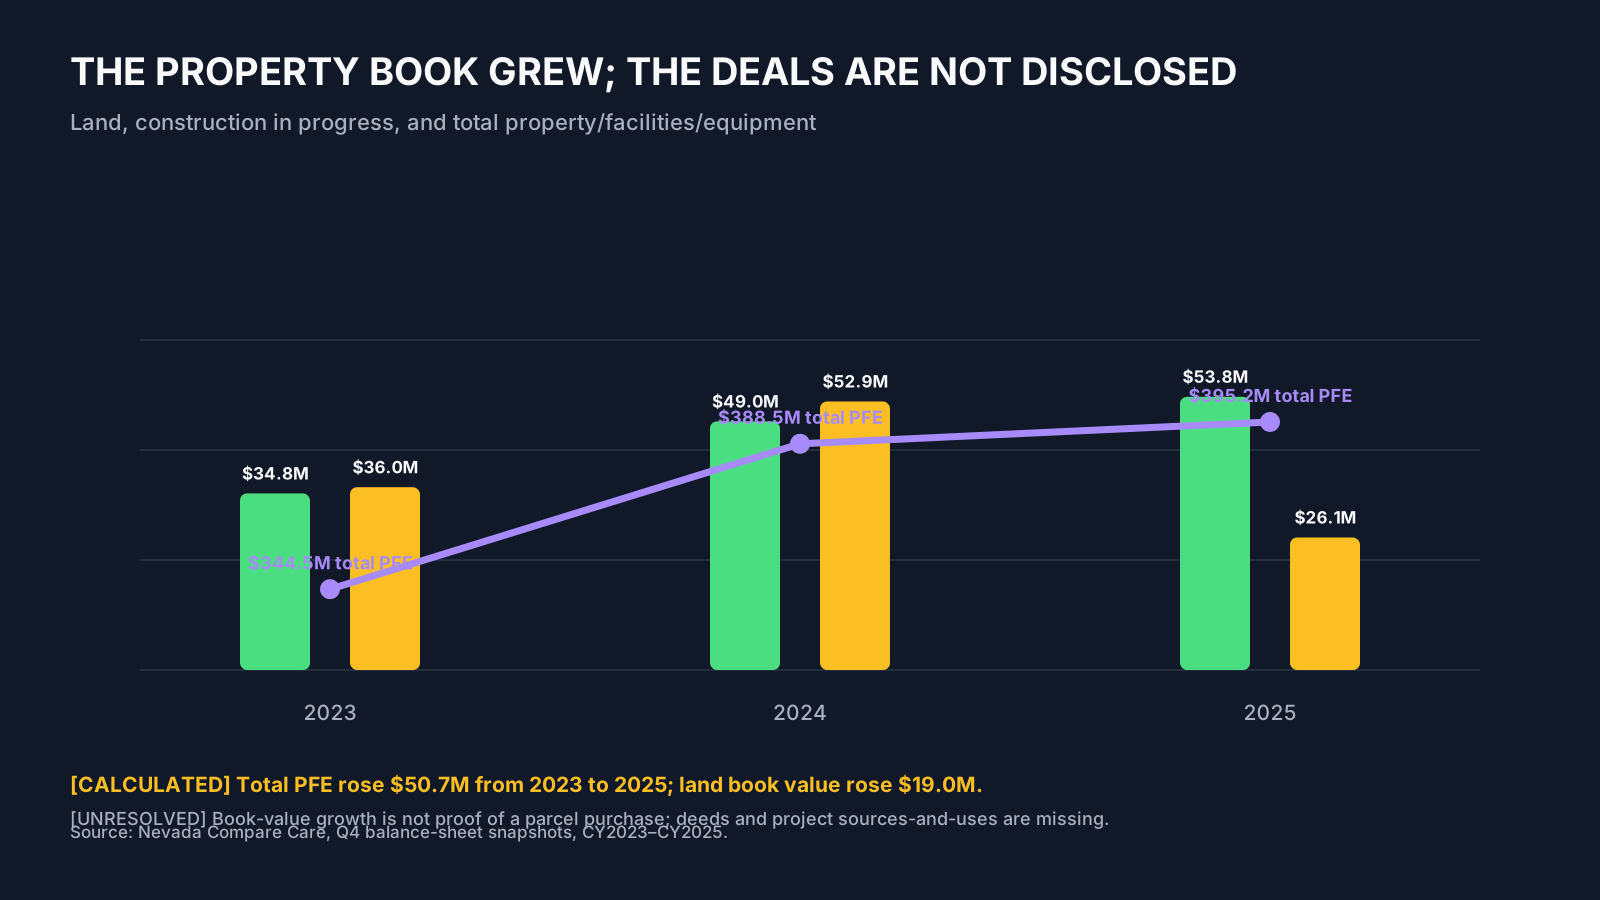
2023 capital spending:$47.3M — expansions $12.1M, equipment $3.8M, other $31.4M. Property/facility/equipment book value rose $344.5M → $395.2M from 2023–2025; 2025 construction-in-progress was $26.1M.
A historical multi-phase expansion was reported at about $200M, including $131M for ED/trauma work. Sunrise gained adult Level I trauma designation in April 2026. The network also operates freestanding EDs and CareNow sites.
Answer: Much of this can plausibly be clinical/access capacity. Capital and wages are not perfectly interchangeable, but priorities and returns are fair bargaining questions.
Q8 · Is Sunrise heavily relying on temporary nurses?
Q4 employed / contracted RN FTE:
2022: 1,226.5 / 138.3
2023: 1,333.2 / 80.0
2024: 1,394.0 / 60.0
2025: 1,375 / 35 — combined 1,410
Counterevidence: contracted RN FTE fell 74.7% from 2022 to 2025. That does not support a simple claim of rising agency dependence. But from 2024 to 2025, admissions rose 4.38% while combined RN FTE fell 3.03%, a workload signal worth examining.
Sources: Nevada hospital staffing/volume filings. These are FTEs, not shift-level ratios.
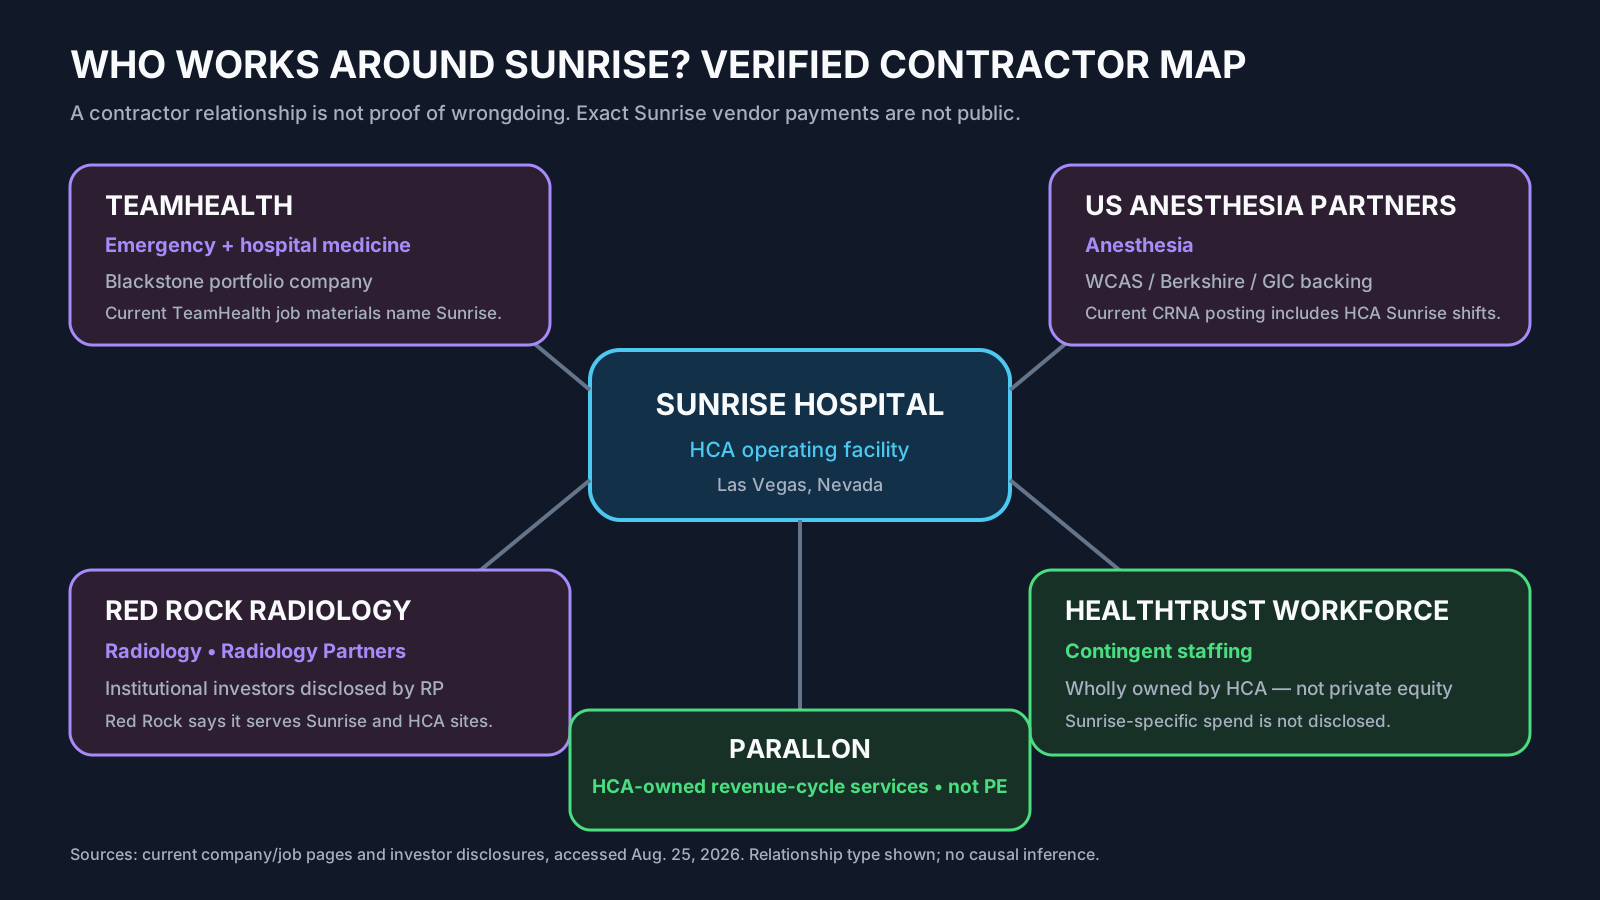
Q9 · Which private-equity or related contractors are present?
Verified service relationships:
TeamHealth / Blackstone: emergency + hospital medicine
US Anesthesia Partners: anesthesia; backed by WCAS/Berkshire/GIC
Red Rock Radiology / Radiology Partners: radiology; institutional-investor backed
HealthTrust Workforce Solutions: contingent staffing, but HCA-owned—not PE
Parallon: HCA-owned revenue-cycle services, not PE
No PE-backed Sunrise parking vendor was identified. Exact Sunrise vendor dollars are not disclosed; professional fees and purchased services cannot be allocated by vendor from public filings.
sunrise property book values 2023 2025.svgsunrise staffing volume 2022 2025.svgsunrise contractor map 2026.svgteamhealth sunrise em job.png
Q10 · How important is Sunrise to HCA? What did the CEO make?
HCA 2025: revenue $75.600B; net income $6.784B; share repurchases $10.067B; dividends $679M; capital spending $4.944B. CEO Sam Hazen compensation: $26,456,606.
Sunrise operating revenue was approximately 1.66% of HCA consolidated revenue, but that is a rough cross-scope comparison—not a cash-flow bridge. A third party placed Sunrise #8 among HCA hospitals using a different, unclear-period revenue measure; treat it as indicative, not definitive.
Local Sunrise CEO compensation and the exact share of HCA profit attributable to Sunrise are not publicly disclosed.
Q11 · Did the 2025 profit come from overcharging patients?
2025 gross/list charges were $15.709B. Contractual/other deductions were $14.459B (92.04%), leaving $1.251B net patient revenue — only 7.96% of list charges. The 12.9× markup is therefore a list-price signal, not the amount collected.
Private-pay gross charges were $1.103B; reported charity deductions $418.3M, bad debt $91.3M, and other contractual adjustments $1.699B. The filing’s uninsured-discount line was $0, an audit question because discounts may be classified elsewhere.
Verdict: high prices warrant scrutiny, but summary filings do not prove the $220.5M profit came from unlawful patient overcharging.
Q12 · Quality, safety, and the final answer
Current CMS release (Apr. 2026): 2 stars. Mortality measures were generally better/no different; readmission was weaker. Lown grades: outcomes A, safety A, satisfaction D, equity C, social responsibility B. The 2021 Leapfrog C is historical; current Leapfrog staffing measures were listed as “did not measure.”
Final answer: Public finances do not substantiate a blanket “unable to pay” claim. They support a demand for transparent costing and a priorities explanation. They do not, alone, prove fraud, unlawful bargaining, or that every capital project should have been redirected to wages.
sunrise revenue share and raise cost.svg
Attached source
Sunrise Nurse Pay and Accountability Addendum 2026-08-25.md